This article is for informational purposes only and does not constitute medical advice. Always consult a qualified spine specialist before making any treatment decisions.
Spinal fusion is a permanent, major surgery. It removes motion from one or more spinal segments, introduces hardware into the spine, and initiates a biological process that takes months to years to complete, with no assurance it will succeed. Patients being evaluated for fusion deserve a complete picture of what can go wrong, not a reassurance that complications are rare and manageable.
Some are rare. Many are not. In over 30 years of spine surgery, including reviewing the cases of patients who came to Deuk Spine Institute after fusion failed them, I have seen how much a complete picture of these risks matters before a patient consents.

Diagnosis. Answers. Relief.
Submit your MRI for a free expert review by Dr. Ara Deukmedjian, M.D., a board-certified neurosurgeon. No obligation. Real answers.
Schedule Yours Today 2,700+ procedures · Zero major complications · No cost, no obligationShort-Term Spinal Fusion Complications
Infection
Open spinal fusion surgery involves deep exposure of vertebral bone, paraspinal musculature, and implanted hardware. The infection rate in open fusion is approximately 1 to 2 percent, with some studies reporting higher rates in patients with diabetes, obesity, or prior spine surgery.
Deep wound infections in fusion surgery are serious. They can involve the implanted hardware, require additional surgical debridement, and in some cases necessitate hardware removal before the fusion has solidified.
Hardware Misplacement
Pedicle screws, rods, and interbody cages must be positioned with accuracy. Misplaced hardware can compress nerve roots, irritate adjacent structures, or fail to provide the mechanical stabilization the fusion requires. Revision surgery to reposition hardware carries all of the risks of the original procedure plus the added complexity of operating through prior scar tissue.
Nerve Damage
Spinal fusion requires retraction of nerve roots adjacent to the spinal cord. Nerve injury during fusion can produce new radicular pain, numbness, or weakness that was not present before surgery.
In some cases this is temporary. In others it is permanent. Patients who undergo fusion for leg pain may find their preoperative nerve symptoms replaced by different ones caused by the surgery itself.
Excessive Bleeding
Fusion requires stripping muscle from bone and, in many cases, removing bone to reach the disc space, and every exposed surface can bleed. The amount of blood lost depends on how many levels are fused, how complex the procedure is, and individual patient factors. Significant blood loss can lead to anemia, a shortage of red blood cells that slows recovery, and may require a transfusion.
The most difficult bleeding to control comes from the epidural venous plexus, the network of veins surrounding the spinal cord. Damage to these veins can obscure the surgical field and place nearby nerves at risk. Injury to a major blood vessel near the spine is rare, but it can cause rapid, life-threatening bleeding.
Blood Clots
Deep vein thrombosis is a recognized risk of any major lower extremity or lumbar spine surgery, particularly in patients with reduced mobility during recovery. Pulmonary embolism, where a clot travels to the lungs, is a potentially life-threatening complication. Extended immobilization during the fusion recovery window, which spans three to twelve months for complete bone healing, increases this risk relative to same-day outpatient procedures.
Dural Tear and Cerebrospinal Fluid Leak
The dura mater is the membrane surrounding the spinal cord and nerve roots. It can be torn during the surgical exposure required for fusion.
When this occurs, cerebrospinal fluid leaks into the wound, requiring primary repair and potentially extending the operative time, increasing infection risk, and prolonging recovery. Undetected or inadequately repaired dural tears can cause positional headaches, nerve irritation, and ongoing fluid accumulation.
Heart and Lung Complications
Like any major operation performed under general anesthesia, spinal fusion carries a risk of heart attack and other cardiac events. These events are uncommon, but when they occur after lumbar fusion they can be fatal.
Pneumonia is a recognized risk during recovery. Anesthesia reduces lung volume and the drive to breathe deeply, and incision pain and limited mobility afterward make it harder to take full breaths and clear secretions. This can lead to atelectasis, a partial collapse of lung tissue that creates conditions where infection can develop.
Failed Fusion: Non-Union and Pseudarthrosis
Spinal fusion depends on the body growing bone tissue across the treated vertebral segment to create a solid, permanent bridge. This process does not always succeed.
Non-union, also called pseudarthrosis, occurs when the bones fail to fuse despite the presence of hardware and bone graft material. Published rates range from approximately 5 to 10 percent, with higher rates in multi-level fusions, smokers, patients with osteoporosis, and those with prior failed fusion attempts.
A failed fusion does not always produce symptoms immediately. In some patients it is discovered on imaging during follow-up. In others it manifests as ongoing pain at the surgical site, hardware loosening, or rod fracture.
The standard treatment for symptomatic non-union is revision fusion surgery, which carries all of the original risks plus the added surgical complexity of revising a prior construct. Patients who experience pseudarthrosis often face a second major surgery to address the failure of the first.
Adjacent Segment Disease
Adjacent segment disease is one of the most documented long-term consequences of spinal fusion. When motion is eliminated at one or more spinal levels, the biomechanical load that was previously distributed across those segments transfers to the vertebrae immediately above and below the fusion. Over time, this accelerated stress degrades the discs, facet joints, and ligamentous structures at those adjacent levels.
Research published in the spine surgery literature documents adjacent segment disease developing in a meaningful percentage of fusion patients over five to ten years post-operatively. The progression varies by the number of levels fused, the patient’s pre-existing degeneration at adjacent levels, and activity level during recovery and afterward. For patients who undergo multi-level fusion, the risk compounds with each additional fused segment.
Adjacent segment disease frequently requires additional intervention, including injections, physical therapy, or further surgery. In some cases patients who initially had a one-level fusion find themselves eventually recommended for extension of that fusion to address the adjacent levels that have degenerated under the redistributed load. The fusion that was supposed to resolve the problem creates the conditions for the next problem.
Failed Back Surgery Syndrome After Fusion
Failed Back Surgery Syndrome describes patients who have spine surgery and experience no meaningful improvement, partial improvement followed by regression, or pain that is worse after the procedure than before. It is a clinical reality, not a fringe outcome. Fusion is one of the most common procedures associated with it.
The most frequent underlying cause is a mismatch between the surgical target and the actual pain source. Fusion addresses structural instability, severe disc collapse, or deformity correction.
When patients whose primary pain comes from disc inflammation or posterior annular tear pathology are recommended for fusion instead, the surgery modifies the structural anatomy without treating the inflammatory driver. The pain remains because the source remains.
Patients who develop Failed Back Surgery Syndrome after fusion often cycle through pain management, repeat injections, spinal cord stimulators, and additional surgical consultations. Some are told their remaining pain is not surgically addressable and are placed on long-term opioid regimens. The physical and quality-of-life consequences of this trajectory are serious and frequently irreversible.
Hardware Complications
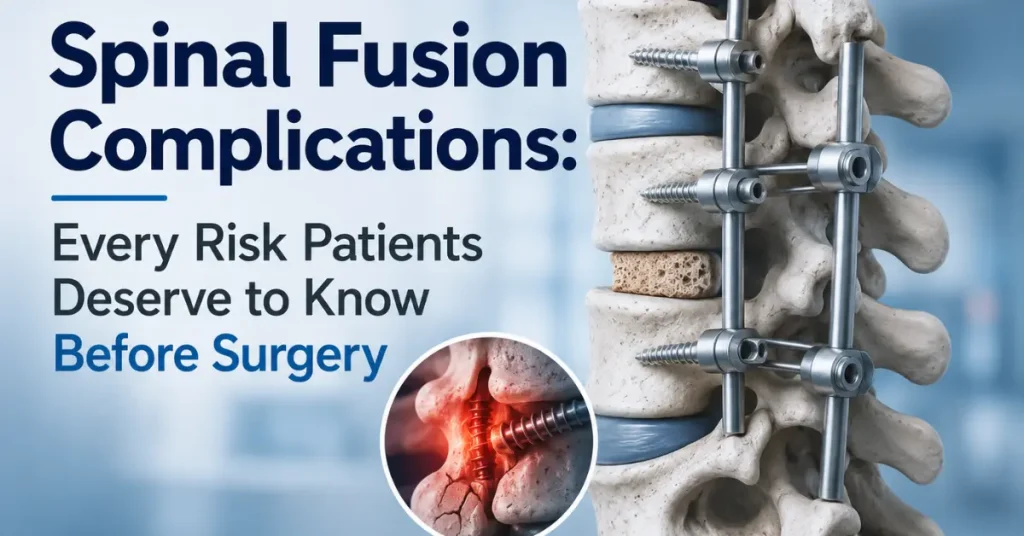
Spinal fusion hardware, including pedicle screws, connecting rods, and interbody cages, is designed to remain in the spine permanently. In practice, hardware complications occur with documented frequency:
- Screw loosening occurs when the bone-screw interface fails to maintain fixation, producing local pain, instability, and sometimes neurological symptoms from screw migration
- Rod fracture develops under the cyclical loading of daily movement, particularly in multi-level constructs or patients with non-union at one of the fused levels
- Cage migration can occur when an interbody device shifts from its implanted position, potentially compressing adjacent neural structures
- Screw pullout is a risk in patients with osteoporosis or poor bone quality, where the bone cannot maintain purchase on the implanted hardware
Each of these complications typically requires revision surgery. Operating through a prior fusion construct, through established scar tissue and around hardware that may have altered local anatomy, is technically more demanding than the original procedure and carries elevated complication risk. The symptoms of failed hardware and the treatment options that follow are covered in our guide to spinal fusion hardware failure.
Permanent Mobility Loss
Every vertebral level included in a fusion is permanently immobilized. This is the intended effect of the surgery, and it is also one of its most lasting consequences. Patients frequently underestimate how motion elimination at even a single lumbar level affects their daily range of movement.
Single-level fusion at L4-L5 or L5-S1 may produce changes that are subtle in daily life but noticeable in bending, lifting, and rotational movement. Multi-level fusion compounds this considerably.
Patients who undergo two-, three-, or four-level fusion procedures lose meaningful portions of their lumbar range of motion permanently. Activities that required spinal flexibility, from athletic pursuits to occupational demands, may no longer be possible at prior levels of function.
The body compensates for lost motion by recruiting movement from other regions, which contributes to the accelerated wear at adjacent segments described above. The immobility imposed by fusion is not localized to the fused levels. Its biomechanical effects radiate through the entire kinetic chain.
Other Common Problems After Spinal Fusion
Beyond the complications above, several problems after spinal fusion develop gradually as the body adapts to a fused segment. Some appear months after surgery. Others take years to become symptomatic.
Muscle Injury and Atrophy
Open fusion requires cutting or retracting the paraspinal muscles, the muscles that run alongside the spine and support it. Prolonged retraction and damage to the nerves that supply these muscles can cause atrophy, a loss of muscle mass, and fatty degeneration, where muscle tissue is replaced by fat. Weakened muscles provide less support to the spine and are a recognized source of ongoing pain after surgery.
Because the fused levels no longer move, the muscles that once controlled them have less work to do and can continue to weaken over time. Recovery of muscle function takes months, and in some patients the pain does not fully resolve.
Flat Back Syndrome
A healthy lumbar spine has a natural inward curve called lordosis, which keeps the body’s center of gravity balanced over the hips. If the lumbar spine is fused in a position that reduces this curve, the result is flat back syndrome, a form of sagittal imbalance, meaning the spine is misaligned from front to back. Patients may lean forward, struggle to stand upright without bending their knees, and develop progressive back pain and fatigue as their muscles work harder to compensate.
Sacroiliac Joint Pain
The sacroiliac (SI) joints connect the base of the spine to the pelvis and normally move very little. When lumbar levels are fused, the forces those levels once absorbed shift downward to the SI joints. This added stress can inflame the joint and produce pain in the low back, buttock, or hip that can be mistaken for pain from the fusion itself.
Research has found that the SI joint is a source of pain in a meaningful share of patients who continue to hurt after lumbar fusion. Identifying it requires a targeted examination, because treating the fused levels again will not relieve pain that originates in the SI joint.
Scar Tissue Around the Nerve Roots
Epidural fibrosis is scar tissue that forms around the nerve roots after spine surgery. Scar tissue is a normal part of healing and has no nerve endings of its own, but when it forms excessively it can tether or compress a nerve root and cause inflammation. It is one of the recognized contributors to Failed Back Surgery Syndrome.
Recovery Complications
Spinal fusion recovery spans three to twelve months for complete bone healing, with restrictions on bending, lifting, and twisting throughout that window. This extended recovery period introduces its own category of complications:
- Opioid dependence is a documented risk during multi-month fusion recovery. Pain management during the healing window routinely involves opioid medications, and patients on these medications for extended periods face dependency risk that may continue beyond surgical recovery
- Physical therapy non-compliance during the healing window can produce muscle atrophy, deconditioning, and adhesion formation around the surgical site that impairs long-term outcomes
- Re-injury during healing occurs when patients return to activity before bone bridging is complete, disrupting the fusion process and potentially requiring revision
- Psychological impact of extended activity restriction, particularly for active patients, contributes to depression and anxiety that complicate recovery outcomes
The recovery window for fusion is not a brief inconvenience. It is a period measured in months where daily life is meaningfully restricted, pain management carries its own risks, and the outcome of the surgical investment remains uncertain until imaging confirms whether fusion has occurred.
An Alternative Without Hardware or Fusion
The Deuk Laser Disc Repair® procedure treats disc-driven back pain at its structural source, the posterior annular tear and the inflammation it generates, without removing bone, implanting hardware, or eliminating spinal motion. In over 2,700 procedures, the complication rate is 0.01% and the infection rate is 0%. Patients are discharged the same day with no fusion hardware to loosen, no adjacent segment to overload, and no extended recovery window during which opioid dependence can develop.
The comparison is not between a safe surgery and a risky one. It is between a surgery matched to a confirmed diagnosis and one recommended before the pain source has been confirmed.
Fusion addresses mechanical instability, deformity, and severe structural failure. When recommended for disc pain from annular tear inflammation, it exposes the patient to every complication above while leaving the actual pain generator untreated.
| Factor | Spinal Fusion | Deuk Laser Disc Repair® |
|---|---|---|
| Hardware complications | Screw loosening, rod fracture, cage migration | No hardware implanted |
| Mobility loss | Permanent at all fused levels | Full motion preserved |
| Recovery window | 3-12 months, activity restricted | Same-day discharge, ambulatory within hours |
Before You Consent to Fusion
If you are evaluating spinal fusion complications and risks before committing to surgery, the most important question is whether the disc is confirmed as your pain source and whether fusion is the only option that addresses it. For many patients, it is not.
Disc pain originating from posterior annular tear inflammation does not require hardware, bone graft, or permanent motion elimination to treat. It requires a procedure that targets the tear and removes the inflammatory tissue, which is exactly what Deuk Laser Disc Repair® does. Understanding what spinal fusion is, what it changes permanently, and what surgical alternatives exist is the foundation of an informed decision.
Our spinal fusion surgery overview explains how the procedure is performed. For patients exploring options that avoid the fusion complication profile entirely, our alternatives to spinal fusion resource explains what motion-preserving procedures offer and who is a candidate.
Request your free MRI review at Deuk Spine Institute. We will tell you which structure is generating your pain, whether Deuk Laser Disc Repair® can address it, and whether the surgery you have been recommended actually corresponds to your diagnosis. You deserve that information before making a permanent decision about your spine.
Frequently Asked Questions
What are the most common problems after spinal fusion?
The most common problems after spinal fusion include adjacent segment disease, failed fusion (pseudarthrosis), hardware complications such as screw loosening or rod fracture, and persistent pain from Failed Back Surgery Syndrome. Patients also report reduced range of motion at the fused levels and new pain in the sacroiliac joints. Some of these appear in the first weeks after surgery, while others develop over several years.
What is the most common long-term complication of spinal fusion?
Adjacent segment disease is the most documented long-term complication. When vertebrae are fused, the levels directly above and below absorb the motion and load the fused segment no longer carries. Over time this accelerates degeneration at those levels and can lead to disc herniation, spinal stenosis, or facet joint arthritis.
Does pain after spinal fusion mean the surgery failed?
Not necessarily. Persistent pain after fusion can come from non-union, hardware problems, scar tissue around a nerve root, SI joint stress, or a pain source the fusion was never designed to treat. An accurate diagnosis of which structure is generating the pain matters more than the assumption that another fusion is needed.
How is Deuk Laser Disc Repair® different from spinal fusion?
Spinal fusion removes motion at one or more levels by joining vertebrae with bone graft and implanted screws, rods, or cages. Deuk Laser Disc Repair® is a minimally invasive endoscopic procedure that treats the posterior annular tear and the inflammation it generates, without removing bone, implanting hardware, or eliminating spinal motion. It is appropriate only for patients whose confirmed pain source is the disc, which is why diagnosis comes first.
No cost · No obligation
Live Pain Free
Upload your MRI for a free expert review by Dr. Ara Deukmedjian, M.D., a board-certified neurosurgeon. Ten minutes can change your life.
This content is provided for educational purposes only. It does not constitute medical advice, diagnosis, or a recommendation for any specific treatment. Individual results vary. Outcomes with Deuk Laser Disc Repair® apply to patients whose confirmed pain source matches the treated pathology. Consult a qualified spine specialist to determine appropriate treatment for your condition.