

By Dr. Ara J. Deukmedjian, MD
FAANS Board Certified Neurosurgeon
Updated: October 20 2026.
Disclaimer: This article is for educational purposes only and is not a substitute for a formal medical evaluation. Please consult a professional, for personal advice.
Key Points
✓ Up to 84% of asymptomatic adults have a disc bulge on MRI.¹ The finding alone is not a diagnosis.
✓ Disc pain is driven by chemical inflammation, not just compression.²
✓ A disc bulge and a herniated disc are related but distinct findings on the same degenerative spectrum.³
✓ Symptoms following only the nerve root of just the disc level.⁴
✓ Cauda equina symptoms such as numbness in the saddle area and bowel/bladder dysfunction are an urgent surgical situation.⁶
✓ Lumbar disc bulges at L3, L4 and L5 may be resolved in six to twelve weeks with conservative treatment.⁷
✓ Physical therapy can decrease pain and dysfunction.⁹
✓ Spinal fusion is too frequently utilized and increases risks of infection and segmental dysfunctions.¹⁰ ¹¹
✓ Deuk Laser Disc Repair® treats the inflamed disc tissue without hardware or fusion.¹²
What an L3-L4-L5 Disc Bulge Really Means
A lumbar MRI may indicate a disc bulge at the L3-L4, L4-L5 or L5-S1 region. The occurrence of disc bulge is often mistaken. A review study published in the American Journal of Neuroradiology indicated that disc bulges occurred in thirty percent of asymptomatic twenty-year-olds. For asymptomatic eighty-year-olds, this rate increased to eighty-four percent. The presence of a disc bulge in an MRI examination does not necessarily imply that any form of treatment is needed. 1
What matters is whether your bulge is responsible for your pain, weakness, or nerve symptoms. The majority of L3-L4-L5 disc bulges respond to conservative care. A smaller group needs intervention. And when intervention is needed, patients deserve to know that fusion is no longer the only or the safest option. In my practice, I use Deuk Laser Disc Repair® (DLDR) to treat the inflamed disc tissue directly, without hardware, without fusion, and without the complications that come with them.¹²
Your lower back has five bones called vertebrae. These bones are labeled L1 through L5. They sit on top of the sacrum. Between each pair of bones is a disc. This disc acts like a cushion that takes weight. The disc has two parts.
Nucleus pulposus: This is the part of the disc. It is like gel. It helps take pressure.
Annulus fibrosus: This is the part of the disc. It is made of fibers. It holds the part in place.
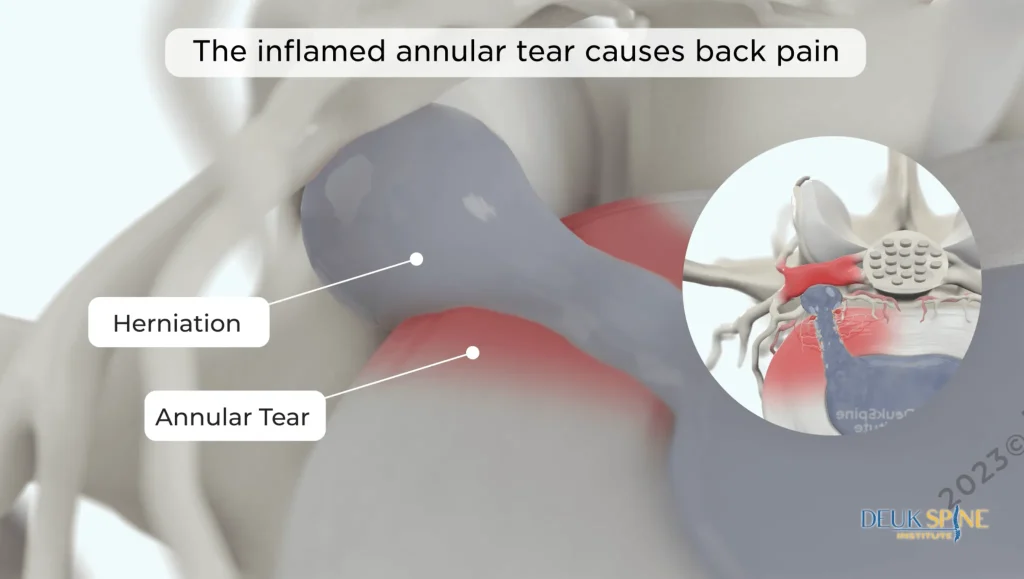
A disc bulge happens when the outer part of the disc gets weak. The disc pushes out past its edge. Usually the disc bulge covers 25 percent or more of the edge. The outer part of the disc stays in one piece. A herniated disc is worse. The outer part of the disc tears. The inner part falls into the space around the spinal cord. Both the disc bulge and the herniated disc are parts of a process that happens over time. The North American Spine Society guidelines treat them related but different problems. ³
Why L3-L4-L5 Takes the Brunt
The lower lumbar discs L3-L4, L4-L5 and L5-S1 carry weight than any part of the spine. The lower lumbar discs are located at the joint where the mobile spine meets the pelvis. Because of this the lower lumbar discs are the places for age-related wear and sudden injury. Data, from the American Association of Neurological Surgeons show that painful disc problems happen at L4-L5 and L5-S1.⁴
Disc Bulges Hurt Because of Inflammation. Not Just Pressure
For many years the theory has been followed in spine surgery which says when the bulging disc squeezes the nerve, pain occurs. This theory alone is inadequate. Recent studies have revealed that pain due to the disc is caused primarily by chemical inflammation and not the disc squeezing pressure. When the outer layer of the disc known as annulus tears, then the inner part of the disc which is known as nucleus releases inflammatory chemicals into the surrounding space². Some of the inflammatory chemicals include Tumor Necrosis Factor alpha, Interleukin-6, Prostaglandins and Substance P and these make the nerve root more sensitive and lead to pain even though the nerves are not being squeezed seen through MRI scans². Therefore a large bulge causes no pain whereas a small tear in the annulus causes severe pain. Hence the best treatment would be treating the tissue rather than just decompressing or inserting metallic hardware. ¹²
Causes and Risk Factors
Disc bulge does not result from trauma. A disc bulge is the end result of multiple interrelated biological and behavioral risk factors.
Degenerative changes due to aging: Disc desiccation refers to loss of water in the core of the disc. It begins during the decade of life. The disc dries out resulting in degeneration of the disc. This explains the increased imaging findings without any symptoms with advancing age.¹
Mechanical loading: Poorly done heavy lifting along with twisting causes pressure on the disc that the disc annulus cannot tolerate repeatedly. Prolonged sitting and bending forward increase disc pressures by more than forty percent compared to standing position.
Smoking: Nicotine reduces blood supply to the discs, thereby increasing disc degeneration and disc healing process.
Obesity: Each additional pound of body weight means added weight to the disc at L4-L5. L5-s1 with each step, bend and lift.
Genetics: Family and twin studies have proven that genes contribute to the risk of disc degeneration regardless of the work done by an individual.
Previous trauma: Trauma caused due to falls, car accidents and sports injuries may lead to tears in the disc annulus that remain asymptomatic for years.
Symptoms by Level: What Your Pain Pattern Is Telling You
Lumbar disc bulging symptoms vary according to the nerve root affected and not the specific disc that is bulging.⁴ Personally, I have seen that the best way to understand the results of an MRI is through the mapping of the symptom pattern to the irritated nerve root. The mapping is the critical process in linking MRI results to the symptoms you experience.
L3-L4 Disc Bulge (L4 Nerve Root)
- Pain across the front of the thigh and down to the inner shin
- Numbness or tingling along the medial lower leg
- Weakness straightening the knee (quadriceps)
- Diminished or absent patellar (knee-jerk) reflex
- A positive femoral nerve stretch test on exam
L4-L5 Disc Bulge (L5 Nerve Root)
- Pain radiating down the outer thigh, outer calf, and top of the foot
- Numbness between the first and second toes
- Weakness lifting the foot in severe cases, foot drop
- Difficulty walking on the heels
- No specific reflex change (L5 has no reliable deep tendon reflex)
L5-S1 Disc Bulge (S1 Nerve Root)
- Pain traveling down the back of the thigh, calf, and into the heel or outer foot
- Numbness along the outside of the foot and the smaller toes
- Weakness pushing off the ball of the foot; difficulty standing on tiptoes
- Diminished or absent Achilles reflex
As stated in the study published in BMJ, pain below the knee and extending into the foot indicates that there are true nerve root complications involved and not merely back problems. It makes it easier to differentiate between the two. The publication is well-renowned within the sphere.⁵
When to Treat Symptoms as an Emergency
Dial 911 and head for the nearest emergency room if any of these symptoms manifest, which might mean you have cauda equina syndrome:⁶
- Loss of bowel or bladder control
- Numbness in the groin, buttocks, or inner thighs (saddle anesthesia)
- Rapidly progressing weakness in one or both legs
- Severe, unrelenting pain unresponsive to any position change
Cauda equina syndrome is a surgical emergency. Delays beyond 24 to 48 hours are associated with permanent neurological deficit.⁶
Diagnosis: Why Imaging Alone Is Not Enough
An MRI report stating the presence of a disc bulge is a diagnostic finding and NOT a diagnosis in itself. Disc bulge is one of the most common entities in patients who have no complaints of any kind; and therefore, a thorough spine evaluation should include three elements:
1. History: onset, progression, duration, provoking and alleviating factors. Previous history of treatment for the same set of symptoms. Sudden lifting causing leg pain gives us a totally different history compared to years of episodic stiffening.
2. Physical examination: Checking the feeling, strength, and reflexes of particular areas of skin and muscles. Such tests as the leg raise test and the femoral nerve stretch test may be used to identify the particular nerve root affected.⁵
3. Imaging: MRI of the spine is the best method of evaluating the disc herniation, any compression of nerve roots, bright areas, indicating inflammation on particular pictures, and dimensions of the spinal canal. Bone imaging such as CT and x-ray are useful for assessing bones’ position. Electromyography and NCS may be recommended when the physical examination findings do not correspond to the results of image diagnostics.
It is only when the findings of history taking, physical examination, and image diagnostics correspond with one another that it is possible to state the cause of pain accurately. The wide variety of decisions concerning the indication for surgery in cases of disc pathologies in the back is a major reason why obtaining a second opinion prior to carrying out an irreversible procedure is critical.
Conservative Treatment: The First Line for Most Patients
Most L3-L4-L5 disc bulges improve without surgery when a comprehensive conservative program is actually followed. The key word is comprehensive isolated interventions almost always underperform combined protocols.
Medications
Ibuprofen, naproxen, and celecoxib which belong to NSAIDs may be used to decrease inflammation at nerve roots. I have noticed that the clinical practice guideline of the American College of Physicians suggests the use of NSAIDs for the treatment of acute and subacute low back pain.⁷ Though the long-term administration of NSAIDs causes some risks associated with cardiovascular and gastric complications, it is necessary to be cautious.
Muscle relaxants like cyclobenzaprine and methocarbamol may be helpful during acute pain in two weeks due to the relief of paraspinal spasm.
Oral corticosteroids on short-term use may reduce radicular inflammation. However, their long-term use is not recommended by me.
Opioids are not indicated in cases of disc pain in the lumbar spine. According to the CDC Guideline for Prescribing Opioids for Pain, there is a danger of dependence. This document also states that opioids have chronic efficacy in treating such pain conditions.⁸
Physical Therapy and Exercise
As demonstrated by a meta-analysis conducted in 2025 in the journal “Frontiers in Medicine”, structured physical therapy provides pain relief, reduces disability, increases range of motion, and improves quality of life in people suffering from lumbar disc herniation.⁹ An effective program should include:
- Core and lumbopelvic stabilization (transverse abdominis, multifidus, gluteals)
- Hip and hamstring flexibility
- Neural mobilization (“nerve glides”) for radicular symptoms
- Postural retraining and ergonomic education
- Gradual return-to-activity progression
Technique matters. Work with a physical therapist experienced in disc pathology. Generic back-pain programs can aggravate an active annular tear.
Lifestyle
Loss of only 5-10% of weight creates a huge difference in the reduction of the burden on the lumbar spine. Stopping the smoking process will aid in restoring the small blood supply in the discs. Altering the working pattern using the sit-stand desk that aids the back along with the correct lifting process will prevent any recurrence. Sleeping in a side lying position and using pillows between the legs or in a supine lying position while using a pillow beneath the knees relieves the spine of pressure.

Injections
Corticosteroids are delivered directly to the location of the affected nerve through epidural steroid injections (ESIs) and selective nerve root blocks. They may be useful for reducing the pain experienced by those suffering from lumbar radiculopathy. However, they cannot solve the problem for good. The procedure does not affect the disc causing the problem. Repeated use of this procedure may weaken the bone and soft tissue structures in the region.
When Conservative Care Isn’t Working
Escalate the evaluation if any of the following develop:
- Pain persists beyond 6 to 12 weeks of appropriate care
- Weakness is new or progressive
- Function and quality of life remain significantly impaired
- Any red-flag symptom (saddle anesthesia, bowel/bladder changes) appears this is an emergency⁶
Surgery: When It’s Appropriate, and the Problem With Fusion
Surgery for an L3-L4-L5 disc bulge is considered when conservative care has failed, when neurologic deficit is progressing, or in true emergencies. The question then becomes: which operation?
Traditional Options
Microdiscectomy removes the fragment of disc pressing on the nerve. It is effective for appropriate candidates but typically requires muscle dissection and partial bone removal to access the disc.
Laminectomy removes a portion of the vertebral lamina to create space for the nerves. Bone removal can reduce spinal stability.
Spinal fusion permanently joins two or more vertebrae with bone graft and metal hardware: screws, rods, and interbody cages. Fusion is the most invasive, most hardware-dependent, and most complication-prone of the standard lumbar operations. The problems are well documented:
- Loss of motion at the fused segment, permanently
- Adjacent segment disease accelerated degeneration above and below the fusion, often requiring further surgery¹⁰
- Hardware complications including loosening, breakage, and pseudoarthrosis (failed fusion)
- Infection risk that is substantially higher than in non-instrumented surgery; as I detailed in my article on infection after spinal fusion, instrumented fusion carries up to a 28% higher surgical site infection rate than non-instrumented procedures.¹¹
- Prolonged recovery typically measured in months, not weeks
Fusion makes sense in a narrow set of cases: true instability, fracture, deformity, tumor. It is vastly overused for routine disc disease.
The Non-Fusion Alternative: Deuk Laser Disc Repair®
I developed Deuk Laser Disc Repair® (DLDR) to treat the actual cause of disc pain. Inflamed nucleus material leaking through an annular tear; without any of the structural destruction that fusion requires.¹²
How the procedure works:
- A small ¼-inch incision is made using anesthesia with mild sedation.
- The tubular retractor is carefully inserted through the muscle fibers without damaging them.
- A high-definition endoscopic camera helps to visualize the tear very well.
- A special medical laser is used to remove the swollen and protruding disc tissue through the tear.
- Healthy discs, bones, ligaments, and muscles are protected from any damage.
- The wound is sutured with one stitch and dressed with a Band-Aid.
Why DLDR avoids the problems of fusion:
- No hardware. No screws, no rods, no cages. Nothing for bacteria to colonize and no hardware-related complications.¹¹
- No fusion. Natural spinal motion is preserved; adjacent-segment disease is not accelerated.¹⁰
- No bone removal. Spinal stability is maintained.
- Outpatient procedure. Patients walk the same day and go home.
- Rapid return to life. Most patients return to desk work within 2 to 3 weeks.
- Documented outcomes. Across more than 1,300 DLDR procedures, we have measured a 95% success rate for appropriately selected patients and a 0.01% complication rate.¹²
Prevention: Protecting L3-L4-L5 for the Long Term
If it is the case of being cured after bulging or prevention of occurrence of bulging, the key factors will still remain the same.
Develop the core. Plank exercises, bird-dogs, dead bugs and McGill Big Three exercises build the strength of supporting muscles.
Lift correctly. Bends at hip level, keeping the weight in proximity of the body, avoiding turning around while holding something heavy.
Sit less. Being in one particular position imposes great strain on the lumbar area of the spine. Stand up, take some steps or just change the position in the period from 30 to 45 minutes.
Sleep in the proper position. Sleep on your side putting a pillow between the knees. If you sleep lying on the back, use pillows under the knees in order not to strain the back.
Drink water and eat anti-inflammatory foods. The discs require hydration; therefore, it would be beneficial to consume anti-inflammatory products and thus help in relieving pains of the spine.
Stay mobile. Exercise regularly doing up to 150 minutes of physical activity per week (walk, swim, ride the bike).
If you are living with pain from an L3-L4-L5 disc bulge. You have more options than most surgeons will offer you. Conservative care works for the majority. For patients who do need surgical intervention. The Deuk Laser Disc Repair® is hardware-free, motion-preserving. It’s a genuine alternative to fusion.
Upload your MRI for a free review and Dr. Deuk will personally evaluate your imaging, correlate it with your symptoms, and walk you through every option. Including the ones your current surgeon may not have mentioned.
Disc pain is driven by chemical inflammation — not just compression. Fusion doesn’t treat inflammation
Your MRI shows a disc bulge.
That’s a finding — not a sentence.
Up to 84% of pain-free adults have a disc bulge on MRI. When an L3-L4-L5 bulge is causing your symptoms, the pain comes from inflamed tissue leaking through an annular tear—not from the bulge itself. Fusion locks down the segment with hardware but never treats the inflammation. DLDR targets only the diseased tissue through a 4 mm incision, preserving your spine’s natural motion.
have a disc bulge on MRI
with instrumented fusion
1,300+ procedures
- Screws, rods & cages implanted permanently
- Loss of motion at fused segment
- Adjacent-segment disease accelerated
- Up to 28% higher infection rate
- 6–12 month recovery
- No hardware, no fusion, no bone removed
- Natural spinal motion preserved
- Treats inflamed tissue at the source
- 0.01% complication rate
- 4 mm incision, same-day outpatient
Board-certified neurosurgeon review · No insurance approval required · 100,000+ procedures performed
FAQ’s
How long does an L3-L4-L5 disc bulge take to heal?
Answer
Symptomatic disc bulges will significantly reduce within six to twelve weeks of appropriate treatment. Large herniations are actually able to go away in its own after three to twelve months through the process wherein the body breaks down the extruded tissue. “Healing” is basically the absence of the pain and not the absence of the finding on the MRI. The finding on the scan might be present for quite some time after the pain disappears. Symptomatic disc bulges can persist despite the presence of pain on imaging after the absence of pain. Herniations are still visible despite no pain present on the imaging.
How do I know if I need surgery for my disc bulge?
Answer
A surgical approach should be considered if any of the following applies to you: 6 to 12 weeks of conservative management have not yielded any significant benefit; weakness in the leg or foot is either new or progressive; pain significantly hampers your daily life; MRI results correlate with your symptoms; or you have developed a “red flag” symptom such as saddle anesthesia or bowel or bladder dysfunction (an emergency situation). Even if all these apply to you, non-invasive hardware-free techniques, like DLDR, will take care of your problem.¹²
Will my disc bulge show on an X-ray?
Answer
No. X-rays are images which show bones, but not disc tissues. It can detect certain indications such as narrowed disc spaces, bone spurs, or instability during flexion and extension views… MRI is the imaging modality to be used to confirm that there is indeed a bulged disc.¹ In case the physician prescribes treatment based solely on X-ray images for suspected disc bulge, then an MRI should be obtained.
Is a bulging disc the same as a herniated disc?
Answer
No. A bulge involves the annulus extending beyond its normal boundary with the outer fibers still intact. A herniation involves a tear in the annulus, with inner nucleus material escaping into the spinal canal. Both can cause radicular symptoms, both exist on the same degenerative spectrum, and both can usually be treated without fusion. The distinction is defined formally in the NASS lumbar disc nomenclature guidelines.³
Will spinal fusion fix my bulging disc permanently?
Answer
Fusion stops motion at the treated segment, but it does not restore a healthy disc, and it introduces a new set of long-term problems adjacent-segment degeneration,¹⁰ hardware complications, and significantly elevated infection risk, as I covered in detail in my article on infection after spinal fusion.¹¹ For most isolated L3-L4-L5 bulges, fusion is more aggressive than the problem requires. A hardware-free laser repair treats the inflamed tissue without any of these downstream costs.¹²
What is the recovery time for Deuk Laser Disc Repair?
Answer
Most patients walk within an hour of the procedure and go home the same day. Light activity resumes within 1 to 2 weeks. Return to desk work is typical at 2 to 3 weeks. Full recovery, including return to higher-impact activity, is generally complete by 4 to 6 weeks. A fraction of the 6- to 12-month recovery arc typical of lumbar fusion.¹²
Is Deuk Laser Disc Repair covered by insurance?
Answer
Coverage varies by carrier and plan. Our team routinely works with major commercial insurance, workers’ compensation, and self-pay patients. For specifics on your plan, see our insurance and financing page.
How do I get a second opinion on my MRI?
Answer
Upload your MRI and symptoms through our Free MRI Review portal. I personally review submitted imaging and, where appropriate, offer a virtual consultation at no charge. If you are a candidate for a non-fusion option, we will tell you. If you are better served by continued conservative care, we will tell you that too.
Sources
View Sources
- 1: https://pmc.ncbi.nlm.nih.gov/articles/PMC4464797/
- 2: https://pmc.ncbi.nlm.nih.gov/articles/PMC10888666/
- 3: https://pubmed.ncbi.nlm.nih.gov/25452112/
- 4: https://www.aans.org/patients/conditions-treatments/herniated-disc/
- 5: https://pmc.ncbi.nlm.nih.gov/articles/PMC1895638/
- 6: https://www.aans.org/patients/conditions-treatments/cauda-equina-syndrome/
- 7: https://www.acpjournals.org/doi/10.7326/M16-2367
- 8: https://www.cdc.gov/opioids/healthcare-professionals/prescribing/guideline/index.html
- 9: https://www.frontiersin.org/journals/medicine/articles/10.3389/fmed.2025.1633762/full
- 10: https://pubmed.ncbi.nlm.nih.gov/15129083/
- 11: https://deukspine.com/blog/infection-after-spinal-surgery
- 12: https://deukspine.com/treatment-options/deuk-laser-disc-repair


