

Dr. Ara J. Deukmedjian, MD
Board Certified Neurosurgeon
Updated: October 27, 2026
Disclaimer: This article is for educational purposes only. It is not a substitute for medical advice, diagnosis, or treatment. Consult your doctor about your spinal health.
Key Takeaways
- Disc extrusion is a severe form of herniated disc in which the gel-like nucleus pulposus breaks through the outer annulus fibrosus and enters the spinal canal.
- The most common sites are L4–L5 and L5–S1 in the lumbar spine and C5–C6 and C6–C7 in the cervical spine. 4 9
- Symptoms range from localized back or neck pain to radiating sciatica, numbness, muscle weakness, and loss of fine motor control.
- Spinal fusion is the default recommendation at most hospitals. Has been associated with up to a 33% higher rate of surgical site infection than non-fusion spine surgery and permanently sacrifices the natural disc. 5
- Deuk Laser Disc Repair® (DLDR) is a 30-minute, outpatient, hardware-free alternative with a 95% success rate across more than 1,300 procedures.
Introduction
Lumbar disc herniation affects between 5 and 20 adults out of 1,000 every year. It is most likely to happen during the fourth and fifth decades of life.
There are more men than women who get this condition with a ratio of about 2 men for every 1 woman. In imaging studies true disc extrusion is found. This is the serious form of herniation where the inner part of the disc breaks, through the whole thickness of the disc wall. This type makes up 25% to 43% of all herniated-disc cases that are found on MRI. 2 3
What Is Disc Extrusion?
The spine supports all activities carried out by the body and maintains the spinal cord together with the nerves which gives sensation and strength to the lower back and neck. There is a disc located between each two vertebrae in the spine. The disc consists of a ring made up of fibrocartilage known as the annulus fibrosis which is made up of a gel like center known as the nucleus pulposus.
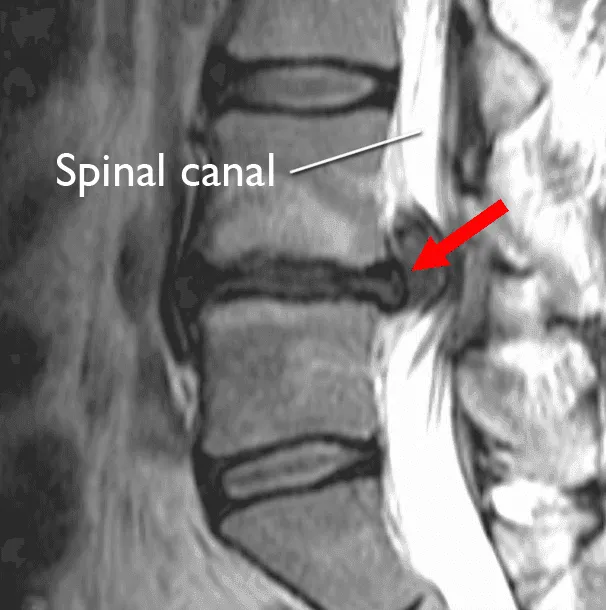
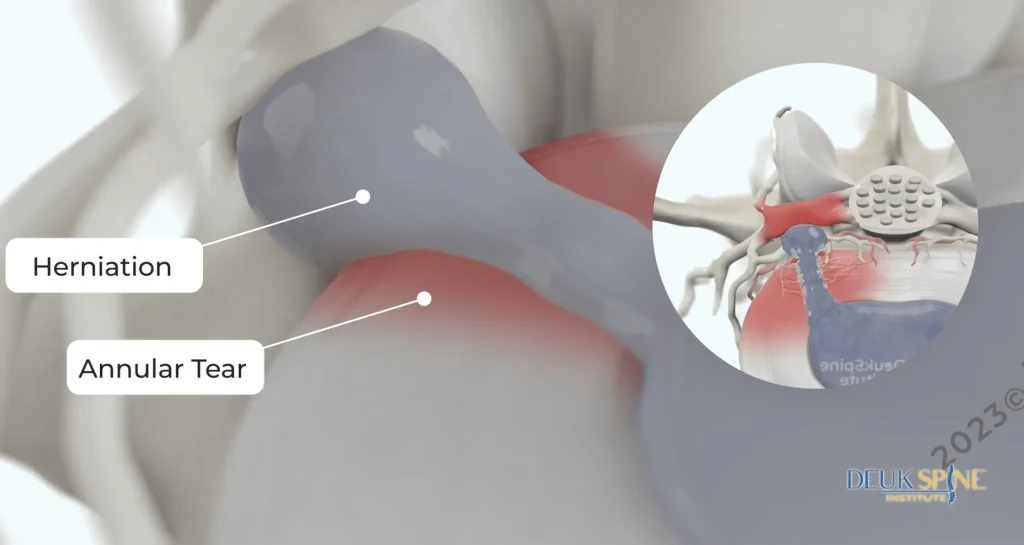
Disc extrusion occurs where there is a tear in the outer portion of the disc called the annulus fibrosis. The soft material inside called nucleus pulposus then bulges out to the spinal canal via the tear. This is not the same with the disc protrusion where the inner material moves without breaking the outer wall.The bulging tissue in case of the extrusion is wider at the margin compared to the base. At times, especially in cases of extreme severity, the bulging piece may detach from the disc. This is called sequestration. 2
When the extruded tissue touches a nerve root or the spinal cord it presses on them. Also triggers a strong inflammatory reaction. This mix of pressure and inflammation is why extrusions usually cause serious symptoms than less severe types of herniation. That’s also why extrusions are often linked to the need for surgery. 3
What Causes Disc Extrusion?
In my practice, disc extrusions almost always arise from a combination of long-term wear and a specific triggering event. The underlying contributors include:
Degenerative Disc Disease. Is a condition that happens when the inner part of a disc, which is called the nucleus pulposus, loses water. It also happens when the outer fibers of the disc, which are called the annulus, lose their stretchiness. Degenerative Disc Disease can begin when people are, in their twenties.
Trauma and sudden loading are risks. If you fall into a car crash or lift something without form the force goes straight into the disc and can crack the weakened annulus.
Repetitive stress and bad posture also hurt. Tech neck, where the head leans forward puts long‑term pressure on the lower neck discs. Often leads to problems at C5–C6 and C6–C7. In the back, constant bending and twisting. Common in jobs like nursing, construction and warehouse work. Speed up damage to the annulus.
Smoking. Nicotine damages the blood flow to the disc. Quickens disc degeneration. Smokers suffer a risk of painful herniation. 7
Sedentary Lifestyle. A sedentary lifestyle. Extra body weight increases the pressure on the lumbar discs. Not moving enough causes the core muscles that support the spine to become weak. Being overweight and having a lifestyle together make the discs, in the lower back break down faster. 7
Genetics. Some people inherit collagen variants that make disc degeneration start earlier and become more severe. Genetics can raise the chance of disc problems. 7
Where Disc Extrusion Occurs in the Spine
Disc extrusions develop most often in the segments of the spine that bear the most load and move through the greatest range of motion. The thoracic spine is the least common site because it is stabilized by the rib cage. 8
Cervical Disc Extrusion
- C4–C5: Wear here commonly produces shoulder pain and deltoid weakness.
- C5–C6: One of the most vulnerable segments in the entire spine, often injured by forward-head posture. Compression of the C6 nerve root causes radiating pain into the thumb and index finger, biceps weakness, and reduced wrist extension.
- C6–C7: This is the most common level in the neck where a disc might push out. Since the C7 nerve root is responsible for the triceps muscle and the middle finger pressure in this area can cause pain and weakness, in those areas.
Lumbar Disc Extrusion
- L4-L5: Discs of the spine get affected frequently. Compression of the L5 nerve root at the L4 and L5 disc level results in pain extending to the feet through the legs. L5 nerve root compression is also known to produce weakness in dorsiflexion, also referred to as foot drop.
- L5–S1: The lumbosacral junction takes on a lot of stress. When the S1 nerve root is compressed it can cause pain that travels down the back of the leg all the way to the heel and the bottom of the foot. There may also be weakness, in the ability to push the foot down which is called plantarflexion. Studies using imaging have shown that L5–S1 is one of the common places where herniated discs happen and cause symptoms. 9
Thoracic Disc Extrusion
Thoracic extrusions are rare. They occur in than one percent of symptomatic disc herniations. When a thoracic extrusion happens it can give you band‑like pain, in the chest or abdomen. Walking may become difficult. In the cases a thoracic extrusion can compress the spinal cord and lead to myelopathy. 8
Symptoms of Disc Extrusion
Symptoms depend on which segment is affected and which nerve root is compressed. The most common presentations I evaluate include:
- Radiating pain in one or both arms or legs
- Numbness or tingling in the hand fingers, foot or toes
- Weakness in a specific muscle group (grip, biceps, quadriceps, calf)
- Losing fine motor control or coordination
- Burning or electric-shock feelings down a limb
- Pain that gets worse when coughing, sneezing or straining
- In very serious cases problems, with the bladder or bowels
Caution signs. It is critical for the patient to have a sudden inability to control his/her bowels and bladder functions and feeling numbness from the thighs to the genital region, this may be an indication of Cauda Equina Syndrome, which requires an urgent surgical intervention. The patient should report to the emergency department. 10
How Disc Extrusion Is Diagnosed
A proper diagnosis requires more than a physical exam. In my office, we follow a three-step process:
- Clinical. Neurological Exam. The Neurological Exam checks strength, reflexes, sensation and gait mapping which nerve root is affected.
- MRI of the Affected Spine. MRI is considered to be the gold standard for the diagnosis of extrusions and differential diagnosis of bulges or protrusions. 2 MRI also reveals the degree of compression of the nerve root or spinal cord.
- Provocative Discography. If imaging shows abnormalities at one level of discography can confirm which disc is actually generating pain before any procedure is considered.
Imaging results must always be connected to the symptoms a person is having. Many people who don’t have any pain have disc problems found on MRI scans. That is why treatment should be decided by a doctor who focuses on what the patient’s feeling, not just what the image shows. 2
Treatment Options for Disc Extrusion
1. Conservative Care (First-Line)
For most patients with mild to moderate symptoms, I recommend a trial of conservative management first:
- Activity modification and ergonomic correction
- Physical therapy focused on core and postural stabilization
- Non-steroidal anti-inflammatory drugs (NSAIDs)
- A short course of oral corticosteroids in severe inflammatory episodes
- Epidural steroid injections in selected cases
I see many extrusions improve over time because the body can gradually reabsorb extruded disc material. When extrusions cause symptoms that last longer, than six to twelve weeks or when extrusions bring on worsening neurological problems then an intervention is needed.
2. Traditional Surgery and Its Hidden Costs
The things back surgeons do: microdiscectomy, laminectomy and spinal fusion have similar problems. Each one cuts through. Takes away bone messes with ligaments and muscles and when it comes to fusion puts in metal parts that stop movement in the area that was treated.
Fusion in particular has been associated with:
- A 33% higher rate of surgical site infection compared with non-fusion spine surgery 5
- Pseudoarthrosis (failed fusion) in a meaningful share of cases, requiring revision surgery 11
- Accelerated degeneration of adjacent discs (“adjacent segment disease”)
- Prolonged recovery, often requiring extended opioid pain management
These costs are difficult to justify when a less destructive option exists.
3. Deuk Laser Disc Repair®. The Safer Alternative
I developed Deuk Laser Disc Repair® (DLDR) to treat disc extrusions without removing bone, implanting hardware, or sacrificing the patient’s natural disc. DLDR is a minimally invasive endoscopic procedure performed through a quarter-inch (7 mm) incision under sedation. Using a high-definition endoscope and a precision laser, I vaporize only the extruded nucleus material and seal the annular tear. Leaving the healthy portion of the disc completely intact. 12
Key advantages of DLDR include:
- 95% success rate across more than 1,300 procedures
- 30-minute average operating time per disc
- No fusion, no hardware, no bone drilling
- Outpatient patients go home the same day with a Band-Aid over the incision
- Virtually bloodless with a 1-hour recovery
- 0.01% complication rate across the institute’s full procedure history
Because DLDR preserves the natural disc, the spine continues to move and function normally and the risks tied to implants (hardware loosening, biofilm-related infection, and adjacent-segment degeneration) are eliminated.
The Better Way Forward
A disk extrusion is a problem but it is not a guarantee of a lifetime of pain or a trip to the operating room for a destructive fusion. With the diagnosis and the proper treatment most people get back to the life they had before the pain started. Without any metal devices, without staying in a hospital and without the long-term issues that come with fusion. a call at 1-800-FIX-MY-BACK.
Disc extrusion means the nucleus has broken through the annulus into the spinal canal — fusion removes the entire disc and locks the segment
An extruded disc is serious.
Destroying it with fusion is worse.
In a disc extrusion, the gel-like nucleus breaks through the full thickness of the annulus and enters the spinal canal—compressing nerves and triggering intense inflammation. Fusion responds by removing the disc entirely, implanting hardware, and locking the segment. DLDR targets only the extruded material with a precision laser through a 7 mm incision, seals the annular tear, and preserves the healthy disc.
are true extrusions
rate with spinal fusion
2,800+ procedures
- Entire disc removed & replaced with hardware
- Segment permanently locked
- 33% higher surgical-site infection rate
- Pseudoarthrosis risk requiring revision
- Extended recovery & prolonged opioid use
- Only extruded material removed; healthy disc kept
- Annular tear sealed by precision laser
- 95% success rate, 2,800+ procedures
- 0.01% complication rate
- 7 mm incision, 30-min outpatient procedure
Board-certified neurosurgeon review · No insurance approval required · 100,000+ procedures performed
FAQ
Q: Is a disc extrusion worse than a bulging disc?
Answer
Yes. A bulging disc remains contained within an intact annulus, while an extrusion is a full-thickness tear with nucleus material pushed into the spinal canal. Extrusions are more likely to compress nerves and more likely to require surgical treatment. 3
Q: Can a disc extrusion heal on its own?
Answer
Smaller extrusions can. Be reabsorbed over weeks and months especially when treatment is conservative. Larger extrusions, isolated fragments or extrusions that create worsening problems normally require procedural treatment.
Q: How long does recovery from Deuk Laser Disc Repair® take?
Answer
Patients typically walk out of our surgery center within an hour of the procedure and resume light activity within days. Significantly faster than recovery from fusion.
Q: Does insurance cover treatment for a disc extrusion?
Answer
Big insurance companies pay for the tests and basic treatments. What they cover for procedures can be different. Our patient services team looks at your insurance and payment choices during your visit.
Q: What symptoms mean I should see a specialist immediately?
Answer
Progressive leg or arm weakness, new numbness in the groin or inner thighs, loss of bladder or bowel control, or pain uncontrolled by medication all warrant urgent evaluation. 10
Q: Can I avoid spinal fusion if I already have a disc extrusion?
Answer
In the vast majority of cases, yes. Most patients who come to Deuk Spine Institute after being told they “need a fusion” turn out to be candidates for DLDR instead.
Sources
View Sources
- Mehta, S. “How common are disc herniations?” Pfizer Health Answers. https://healthanswers.pfizer.com/bone-joint-muscle/back-spine/how-common-are-disc-herniations-video
- Fardon DF, et al. “Lumbar disc nomenclature: version 2.0.” The Spine Journal. https://pubmed.ncbi.nlm.nih.gov/24768732/
- Kim HS, et al. “Prognostic factors in single-level lumbar disc herniation.” Journal of Korean Neurosurgical Society. https://pmc.ncbi.nlm.nih.gov/articles/PMC6835144/
- Multi-level MRI correlation study of lumbar intervertebral disc pathology. Journal of Clinical and Diagnostic Research. https://pmc.ncbi.nlm.nih.gov/articles/PMC4437133/
- Deuk Spine Institute. “The Danger of Infections After Spinal Fusion Surgery.” https://deukspine.com/blog/infection-after-spinal-surgery/
- Adams MA, Roughley PJ. “What is intervertebral disc degeneration, and what causes it?” Spine. https://pubmed.ncbi.nlm.nih.gov/17077740/
- Abril Mera TM, et al. “Prevalence of Herniated Discs and Risk Factors in Patients with Low Back Pain.” Ciencia Latina. https://doi.org/10.37811/cl_rcm.v9i4.19252
- Brown CW, et al. “The natural history of thoracic disc herniation.” Spine. https://pubmed.ncbi.nlm.nih.gov/1529280/
- Zhao Y, et al. “Prevalence of lumbar disc herniation in populations with different symptoms based on magnetic resonance imaging study.” Journal of Clinical Neuroscience, Nov 2024. https://pubmed.ncbi.nlm.nih.gov/39326345/
- Mayo Clinic. “Cauda Equina Syndrome — Symptoms & Causes.” https://www.mayoclinic.org/
- Deuk Spine Institute. “Pseudarthrosis After Fusion: What It Means When the Bone Never Joins.” https://deukspine.com/blog/pseudarthrosis-after-fusion/
- “Precision laser applications in spine surgery.” PubMed. https://pubmed.ncbi.nlm.nih.gov/23776754/


